
Attention: Restrictions on use of AUA, AUAER, and UCF content in third party applications, including artificial intelligence technologies, such as large language models and generative AI.
You are prohibited from using or uploading content you accessed through this website into external applications, bots, software, or websites, including those using artificial intelligence technologies and infrastructure, including deep learning, machine learning and large language models and generative AI.
2026 Merit-based Incentive Payment System (MIPS) Value Pathways (MVP) Toolkit
NOTE: This toolkit is for information purposes and summarizes AUA’s understanding of information from the U.S. Centers for Medicare & Medicaid Services (CMS). For official CMS wording, more detailed discussion, and/or up-to-date information on these or related topics, visit the CMS website.
This toolkit provides an overview of the 2026 participation rules, performance categories, and scoring approaches for the Merit-based Incentive Payment System (MIPS) Value Pathways (MVP) reporting option. It also describes the three options that are supported by AUA’s Quality Registry (“AQUA”) in 2026 (i.e., Advancing Cancer Care, Focusing on Women’s Health, and Optimal Care for Patients with Urologic Conditions).
A separate Merit-based Incentive Payment System (MIPS) toolkit explains the Traditional Merit-based Incentive Payment System (MIPS) reporting option in detail.
MIPS Background
The Medicare Access and CHIP Reauthorization Act of 2015— also known as MACRA—was signed into law on April 16, 2015. This law, which created the Quality Payment Program (QPP), changed the way physicians are paid for providing services under Medicare. It continued the move away from fee-for-service payment, toward value-based payment approaches that endeavor to pay clinicians based on the quality, value, and outcomes of the care they provide.
Eligible clinicians can participate in the QPP through Merit-based Incentive Payment System (MIPS) or Advanced Alternative Payment Models (APMs). They can complete MIPS reporting through one of three options.
Figure 1. QPP Reporting Options

Clinicians should visit the CMS QPP Participation Status Lookup Tool to determine their MIPS eligibility status. MIPS participation is available through the following options:
- As an individual
- As a part of a group, virtual group, or subgroup
- As an APM Entity
Check out the following resources for more information:
- Quality Payment Program (QPP) Information
- MIPS Eligibility Information
- Exceptions to MIPS Participation
- Special Statuses (for MIPS Participation)

Traditional MIPS Overview
Figure 2. MIPS Performance Categories for Individuals, Groups, and Virtual Groups

NOTE: Performance category weights vary based on the participation option. Weights also vary for small practices that do not submit PI data or when re-weighting is applied (e.g., due to hardship exemptions or extreme and uncontrollable circumstances).
MIPS-eligible clinicians earn payment for Medicare Part B covered professional services based on four performance categories:
- The Quality category assesses the quality of care by measuring health care processes, outcomes, and patient experiences of care.
- The Cost category assesses the cost of the care based on your Medicare Part B Claims
- The Improvement Activities (IA) category assesses participation in activities that improve clinical practice and support practice engagement.
- The Promoting Interoperability (PI) category assesses promotion of patient engagement and electronic exchange of health information using certified electronic health record technology (CEHRT).
CMS scores each performance category separately. The final MIPS score, which ranges from 0 to 100 points, is calculated by adding together the final scores for each of the four performance categories.
Table 1. Performance Category Weights by MIPS Reporting Option

Each performance category has an assigned weight used in calculating a final MIPS score. The performance category weights are the same for the Traditional MIPS and MVP reporting options. Participants reporting through either option will be scored on all four performance categories. In contrast, the final MIPS score excludes the Cost category for APM Entities and excludes the Promoting Interoperability category for small practices.
MIPS is a budget-neutral program, meaning the positive payment adjustments (bonuses) are funded through the negative payment adjustments (penalties). The performance threshold for 2026 remains 75 points (out of 100). Participants need a score higher than 75.00 points to receive a positive payment adjustment (bonus).
Table 2. 2026 MIPS Payment Adjustments

(Source: MIPS Payment Adjustments)
Check out the following resource(s) for more information:

MIPS Value Pathways (MVPs) Overview

(Source: U.S. Centers for Medicare & Medicaid Services)
The Centers for Medicare and Medicaid Services (CMS) notes that MVPs offer more meaningful groupings of measures and activities, to provide a more connected assessment of the quality of care. MVPs include the same four performance categories as Traditional MIPS (i.e., Quality, Cost, Improvement Activities, and Promoting Interoperability). However, the quality measures, cost measures, and improvement activities that are included in a particular MVP have been selected based on their alignment with the focus of the MVP (i.e., a specific condition or specialty).
- Most MVPs are limited to 10-20 quality measures, 1-3 cost measures, and 10-20 improvement activities.
- The “foundational layer” of all MVPs includes the Promoting Interoperability performance category, where the measures and attestations are identical to those in Traditional MIPS, as well as two population health measures that CMS calculates based on administrative claims. The measures and attestations in the foundational layer are identical across all MVPs.
- Beginning in 2025, participants no longer have to select a population health measure during the registration process. Instead, CMS will calculate both measures if the case minimum is met and use the higher score.
Voluntary MVP and subgroup reporting began in 2023. Beginning in 2026, any multispecialty groups reporting MVPs must report as subgroups or as individual MIPS eligible clinicians.

(Source: CMS)
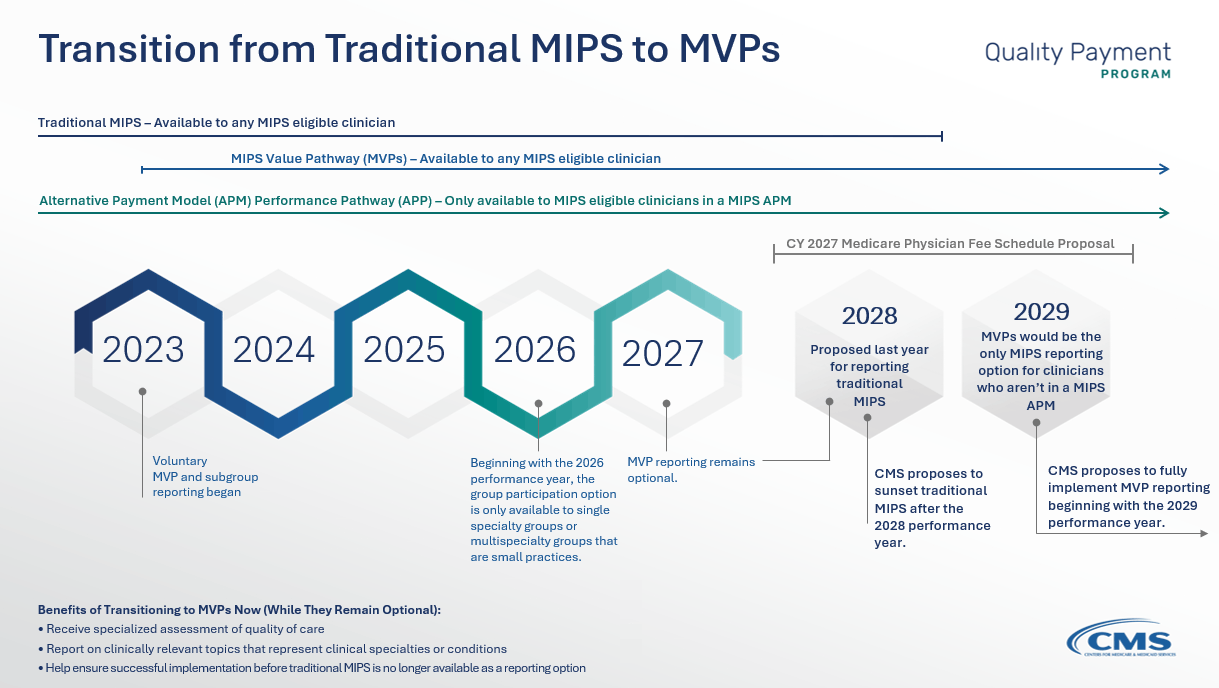
CMS plans to sunset Traditional MIPS in the future, at which point MVP reporting will become mandatory, unless the clinician is eligible to report via the APP. There are 27 finalized MVPs available for the 2026 performance year.
Check out the following resource(s) for more information:

MVP Participation Options
Providers may be eligible to participate in MIPS via MVPs as an individual MIPS eligible clinician, as part of a group (single specialty and multispecialty), as part of a subgroup, or as an APM entity.
- Eligible clinicians can register to report as an individual and as a part of group or subgroup.
- Subgroup participation is required for multispecialty practices reporting MVPs, beginning with the 2026 performance period.
- Multispecialty small practices can report as a group, without forming subgroups, beginning with the 2026 performance period.
Check out the following resource(s) for more information:

MVP Registration
Registration is required to report an MVP.
- The registration window opens on April 1, 2026, and closes at 8:00pm (Eastern) on November 30, 2026.
- A Health Care Quality Information System (HCQIS) Access Roles and Profile system (HARP) account is needed to sign into the QPP website to complete the registration process.
- In addition to identifying a preferred MVP, participants may need to provide additional information about participation options (e.g., group, individual).
- MVP registration for groups requires the submission of information about the group’s specialty composition (i.e., single specialty, multispecialty group).
- Subgroup reporting, which allows a smaller set of clinicians within a practice to report on the same set of measures and improvement activities, is available only if the group meets the minimum criteria (i.e., must include at least 2 clinicians, one of whom must be MIPS eligible). An MIPS eligible clinician is limited to one subgroup per TIN.
Check out the following resource(s) for more information:

Available MVP Options
There are 27 finalized MVPs for the 2026 performance year. This includes the following six new options:
- Diagnostic Radiology
- Interventional Radiology
- Neuropsychology
- Pathology
- Podiatry
- Vascular Surgery
The AQUA Registry supports the following three options:
- Advancing Cancer Care
- Focusing on Women’s Health
- Optimal Care for Patients with Urologic Conditions
Review the individual requirements to learn more about the remaining MVP options.
Check out the following resource for more information:

Performance Categories
MVPs include the same four performance categories as Traditional MIPS (i.e., Quality, Cost, Improvement Activities, and Promoting Interoperability). However, the quality measures, cost measures, and improvement activities that are included in a particular MVP have been selected based on their alignment with the focus of the MVP (i.e., a specific condition or specialty).
Performance Category: Quality

NOTE: Performance category weights vary based on the participation option. Weights also vary for small practices that do not submit PI data or when re-weighting is applied (e.g., due to hardship exemptions or extreme and uncontrollable circumstances).
The Quality performance category focuses on measures that assess health care processes, outcomes, and patient experiences of care. For MVPs, this category includes quality measures and population measures.
- MVP participants must complete the following for the quality measures:
- Report data for at least 4 quality measures from the MVP (one of which must be an outcome measure, or a high-priority measure, in the absence of an applicable outcome measure). Participants can opt to report on more than four measures; in that case, CMS will use the four measures with the highest scores.
- Collect and submit data from January 1, 2026, to December 31, 2026 (i.e., a 12-month period).
- Meet the data completeness requirement, which requires reporting performance data for at least 75% of the denominator-eligible cases, for each measure.
- CMS will calculate two population health measures (included in the “Foundational Layer”) via administrative claims and use the highest of the two scores. If the MVP participant doesn’t meet the case minimum for either population health measure, the measure will be excluded from scoring.
MVP participants may use a combination of the following measure options to complete MVP reporting for the 2026 performance year. Click on the links below for more information.
- Consumer Assessment of Healthcare Providers and Systems (CAHPS) for MIPS Survey Measure
- Electronic Clinical Quality (eCQMs) Measures
- Medicare Part B Claims Measures
- MIPS Clinical Quality (MIPS CQMs) Measures
- Qualified Clinical Data Registry (QCDR) Measures
CMS allows small practices to earn points even if they do not meet quality measure requirements.
- Six (6) bonus points will be awarded for submitting data for at least one quality measure.
- Three (3) points are available for each quality measure that does not meet the case minimum or data completeness criteria.
- Small practices can earn three (3) points for quality measures that lack benchmarks.
Participants earn points for the Quality category based on how their results compare to those of other participants.
- Measure results are compared to benchmarks based on historical data to determine the number of achievable points for submitted measures.
- Next, bonus points are awarded as applicable, and a percentage score is computed.
- Then, the final score for the Quality performance category is calculated by weighting the Quality percentage score by the Quality weight (for 2026, this is 30 percent for individuals, groups, and virtual groups).
- Six bonus points will be awarded to small practices that submit data for at least one quality measure.
Benchmarks are the point of comparison used to score submitted measures. CMS scores each measure by comparing participants’ performance to the benchmark, for a maximum of 10 points. A series of historical benchmarks is established, when possible, for each measure, for each reporting mechanism (e.g., if a measure can be reported as a CQM and an eCQM, it will have two benchmarks). For 2026, those benchmarks were calculated using data reported for 2024.
- If a measure does not have a historical benchmark, CMS will attempt to calculate one using 2026 data. If no historical benchmark exists and one cannot be calculated using 2026 data, CMS will not award any points for that measure, unless the measure in its first or second year in the program.
- Participants may be able to earn as many as 10 additional percentage points if their score for the Quality category improved compared to their score in the previous year.
Check out the following resources for more information:
- 2026 Quality Quick Start Guide
- MIPS Quality Performance Category Fact Sheet
- MVP Implementation Guide
- Quality Performance Category: Collection Types
- CMS Benchmark Files
- Topped-Out Measure Benchmarks Policy (Appendix E)

Performance Category: Cost

NOTE: Performance category weights vary based on the participation option. Weights also vary for small practices that do not submit PI data or when re-weighting is applied (e.g., due to hardship exemptions or extreme and uncontrollable circumstances).
The Cost performance category accounts for 30% of the final MVP score and includes measures that assess the following for Medicare patients:
- Overall cost of care provided, with a focus on the primary care they received.
- Cost of services provided related to a hospital stay.
- Costs for items and services provided during specific episodes of care.
In some instances, the cost performance category will not count as 30% of the final MVP score.
- It will count as 0% for APM Entities who report through an MVP.
- It will also as count as 0% if a participant does not meet the attribution requirements of all available cost measures.
- For individuals or groups exempt from the quality and promoting interoperability categories it will count as 50% of the final MVP Score.
There are 35 cost measures available for the 2026 performance year. Two (2) are population-based and thirty-three (33) are episode-based. CMS did not expand or revise the list of cost measures but updated the candidate event and attribution rules for the Total Per Capita Cost (TPCC) measure
- Population-based cost measures focus on primary and inpatient care. The two (2) population-based cost measures for the 2026 performance year are:
- Total Per Capita Cost (TPCC)
- Medicare Spending per Beneficiary (MSPB) Clinician Measure
- Episode-based cost measures focus on procedures, acute inpatient medical conditions and chronic conditions.
- They include only items and services that are related to the episode of care for a specific clinical condition or procedure, as opposed to all Medicare part A and B services over a specific timeframe. The length of the episode varies, depending on the measure.
- The two episode-based cost measures most applicable to urology are:
- Renal or Ureteral Stone Surgical Treatment
- Prostate Cancer
CMS uses a comparison of performance on a measure to a performance period benchmark to determine measure achievement points. Cost measure benchmarks are calculated using performance period data (rather than historical data). To receive a score for the cost performance category, participants must meet the established case minimum and be scored on at least one measure. There is a maximum cost improvement score of 1 percentage point available for the Cost performance category.
CMS launched a 2-year information-only feedback period for new cost measures, starting with the 2026 performance period. This new initiative allows clinicians to have access to new measure feedback without it affecting their scores. However, this change is moot for 2026 because CMS did not add new cost measures for the 2026 performance period.
Check out the following resource(s) for more information:

Performance Category: Improvement Activities (IA)

NOTE: Performance category weights vary based on the participation option. Weights also vary for small practices that do not submit PI data or when re-weighting is applied (e.g., due to hardship exemptions or extreme and uncontrollable circumstances).
The Improvement Activities performance category measures participation in activities that improve clinical practice, care delivery, and outcomes. For MVP reporting, completing one improvement activity is required to obtain full credit.
- The IA must be a part of the selected MVP.
- It must be implemented for at least one continuous 90-day performance period (during 2026) unless otherwise stated in the activity description.
- The IA must begin no later than October 3, 2026 (to have a full 90-day performance window).
- A maximum of 40 points is available when attesting to an improvement activity.
Prior to selecting IAs, practices should analyze their practices to identify:
- What areas within the practice need improvement?
- What changes would help to improve the patient’s experience?
- What existing improvement activities could satisfy the IA performance category?
Participants must attest to their IAs, which can be done directly or through a third party such as the AQUA Registry.
- Documentation supporting improvement activities is not required at the time of attestation. However, documentation should be compiled and would be required in the event of a CMS audit.
- Participants must keep this documentation for six years after attestation.
The AUA recommends that participants document as much information as possible about the completed activities. For example:
- If administering a patient satisfaction survey, note in the patient charts who received one and when.
- If attending an Institute for Healthcare Improvement event, save proof of registration and any materials (slides, handouts, etc.) that may have been distributed for the event.
Check out the following resource for more information:

Performance Category: Promoting Interoperability (PI)

NOTE: Performance category weights vary based on the participation option. Weights also vary for small practices that do not submit PI data or when re-weighting is applied (e.g., due to hardship exemptions or extreme and uncontrollable circumstances).
The Performance Improvement (PI) performance category aims to foster the electronic exchange of health information using certified electronic health record technology (CEHRT) through 5 objectives:
- e-Prescribing
- Health Information Exchange
- Provider-to-Patient Exchange
- Public Health and Clinical Data Exchange
- Protect Patient Health Information
The use of technology to exchange and make use of information (i.e., interoperability) can help MVP participants:
- Reduce the burden associated with communicating patient information and, by extension,
- Improve patient access to their health information,
- Improve information exchange between clinicians and pharmacies, and
- Improve the systematic collection, analysis, and interpretation of healthcare data.
Participants must do the following for the PI performance category:
- Use an EHR that meets the National Coordinator for Health Information Technology (ONC) certification criteria specified in 45 CFR 170.315 of the Code of Federal Regulations.
- Collect data for the required measures through their certified EHR technology (CEHRT) for a minimum of 180 continuous days during the calendar year.
The PI exemptions for the 2026 performance period include:
- Automatic reweighting to 0% will apply only to MIPS eligible clinicians, groups, and virtual groups and APM Entities with the following special statuses (which means they are exempt from reporting PI data):
- Ambulatory Surgical Center (ACS)-based
- Hospital-based
- Non-patient facing
- Small practice
- When all their MIPS-eligible clinicians are individually exempt from reporting PI data, groups, virtual groups and APM Entities qualify for automatic reweighting and are exempt from reporting PI data.
- Those who are not automatically exempted must apply for an exception by December 31, 2026. Even if a participant received an exception previously, they must apply again in 2026.
The 2026 performance period includes the following PI exceptions:
- Hardship Exception: Individuals, groups, virtual groups, APM Entities can submit a MIPS PI Performance Category Hardship Exception application to request exemption from reporting PI data due to:
- Using decertified EHR technology
- Having insufficient internet connectivity
- Lacking control over CEHRT availability
- Facing extreme and uncontrollable circumstances
- If a hardship exception is approved, the PI category will receive a weight of 0% when calculating the final score. That 25% will be redistributed to another category unless data is submitted for the PI category.
- Extreme and Uncontrollable Circumstance Exception: Clinicians may also request reweighting to 0% due to a MIPS Extreme and Uncontrollable Circumstance exception. These allow for exemptions due to rare events that are completely outside participants’ control and may apply to multiple performance categories.
Participants must complete the following to avoid receiving a 0 score for the PI performance category:
Figure 3. Promoting Interoperability Requirements

(Source: 2026 MIPS Promoting Interoperability Quick Start Guide)
Table 3. 2026 MIPS Promoting Interoperability Objectives, Measures*, and Available Points

As with the IA performance category, documentation supporting PI reporting is not required at the time of attestation. However, documentation should be compiled and would be required in the event of a CMS audit. Participants must keep this documentation for six years after attestation.
Check out the following resources for more information:
- 2026 MIPS Promoting Interoperability Quick Start Guide (Appendix)
- MIPS Promoting Interoperability Performance Category Fact Sheet
- 2026 MIPS Promoting Interoperability Measure Specifications

Key Differences Between MVP and Traditional MIPS Reporting
The table below highlights key differences between the Traditional MIPS and MVP reporting options. Participants can report via both options; CMS will calculate both scores and use the one with the highest score.
Table 4. Differences Between MVP* and Traditional MIPS*

*In some instances, eligible clinicians may not have to select 2 activities.
For the Promoting Interoperability performance category, there are no differences in the requirements for those who report MVPs or Traditional MIPS. Both groups must report a complete measure set for a continuous 180-day period in the calendar year.
Check out the following resource for more information:

MVP Reporting Through the AUA Quality (AQUA) Registry
The AUA Quality Registry, or AQUA, was developed by urologists and designed to measure, report, and improve healthcare quality and patient outcomes. As a CMS recognized Qualified Clinical Data Registry (QCDR), practices can use AQUA to report MVP information to CMS.
U.S. based practices are eligible to participate in the Registry if they use a compatible electronic health record (EHR) system.
Check out the following resources for more information:
- Learn More About the Benefits of AQUA Registry Participation
- Explore the AQUA Registry Subscription Options
- Learn How the AQUA Registry Supports Solo & Private Practices
- Learn How the AQUA Registry Supports Large Groups and Institutions
- Send an email to AQUA@auanet.org for more AQUA Registry-related information.
MVPs Supported by the AQUA Registry
The AQUA Registry supports 3 of the 27 available MVPs for the 2026 performance year.
- Advancing Cancer Care
- Focusing on Women’s Health
- Optimal Care for Patients with Urologic Conditions
Advancing Cancer Care
This MVP focuses on the clinical theme of providing fundamental treatment and management of cancer care. The measures included assess the following areas: the patient experience of care, end of life care, and appropriate diagnostics along with possible treatment options for different cancer diagnoses.
The AQUA Registry supports the following Quality Payment Program (QPP) measures from the 2026 Advancing Cancer Care MVP.

CMS will calculate the following cost measures if the established case minimum is met or exceeded.

Focusing on Women’s Health
This MVP focuses on the clinical theme of providing treatment and managing women’s health.
The AQUA Registry supports the following Quality Payment Program (QPP) measures from the 2026 Focusing on Women’s Health MVP.

CMS will calculate the following cost measures if the established case minimum is met or exceeded.

Optimal Care for Patients with Urologic Conditions
This MVP focuses on assessing optimal care for patients treated for a broad range of urologic conditions, including kidney stones, urinary incontinence, bladder cancer, and prostate cancer.
The AQUA Registry supports the following Quality Payment Program (QPP) and Qualified Clinical Data Registry (QCDR) measures from the 2026 Urology MVP.

*This is an inverse measure. ** AUA’s most recent guideline on the surgical management of stones no longer supports AQUA14 as currently specified. Therefore, the AQUA Registry strongly recommends using/submitting an alternative measure for PY2026 reporting.
CMS will calculate the following cost measures if the established case minimum is met or exceeded.

(Source: 2026 Summary of Cost Measures)
Check out the following resource(s) for more information:
Additional Contact Information
Contact the CMS Quality Payment Program (QPP) Help Desk for additional information about the Traditional MIPS reporting option (e.g., MIPS eligibility, performance categories, payment adjustments)
- URL: https://qpp.cms.gov/
- Phone: 866-288-8292
- E-mail: QPP@cms.hhs.gov
Contact the AUA Quality & Measurement Department for additional information about the MVP toolkit, Quality Improvement resources, and measures supported by the AQUA Registry.
- URL: https://www.auanet.org/guidelines-and-quality/quality-and-measurement
- E-mail: Quality@auanet.org
Contact the AQUA Registry for additional information about the registration process, subscription options, and participation benefits.
